The diagnosis of chronic pancreatitis is made by a combination of clinical symptoms and imaging studies such as abdominal CT scan, magnetic resonance imaging (MRI), endoscopic ultrasound (EUS) and/or endoscopic retrograde cholangiopancreatography (ERCP).
Chronic Pancreatitis
What are the Symptoms of Chronic Pancreatitis?
- Recurrent abdominal pain (intermittent or constant)
- Greasy or oily stools (steatorrhea)
- Weight loss
Acute Pancreatitis
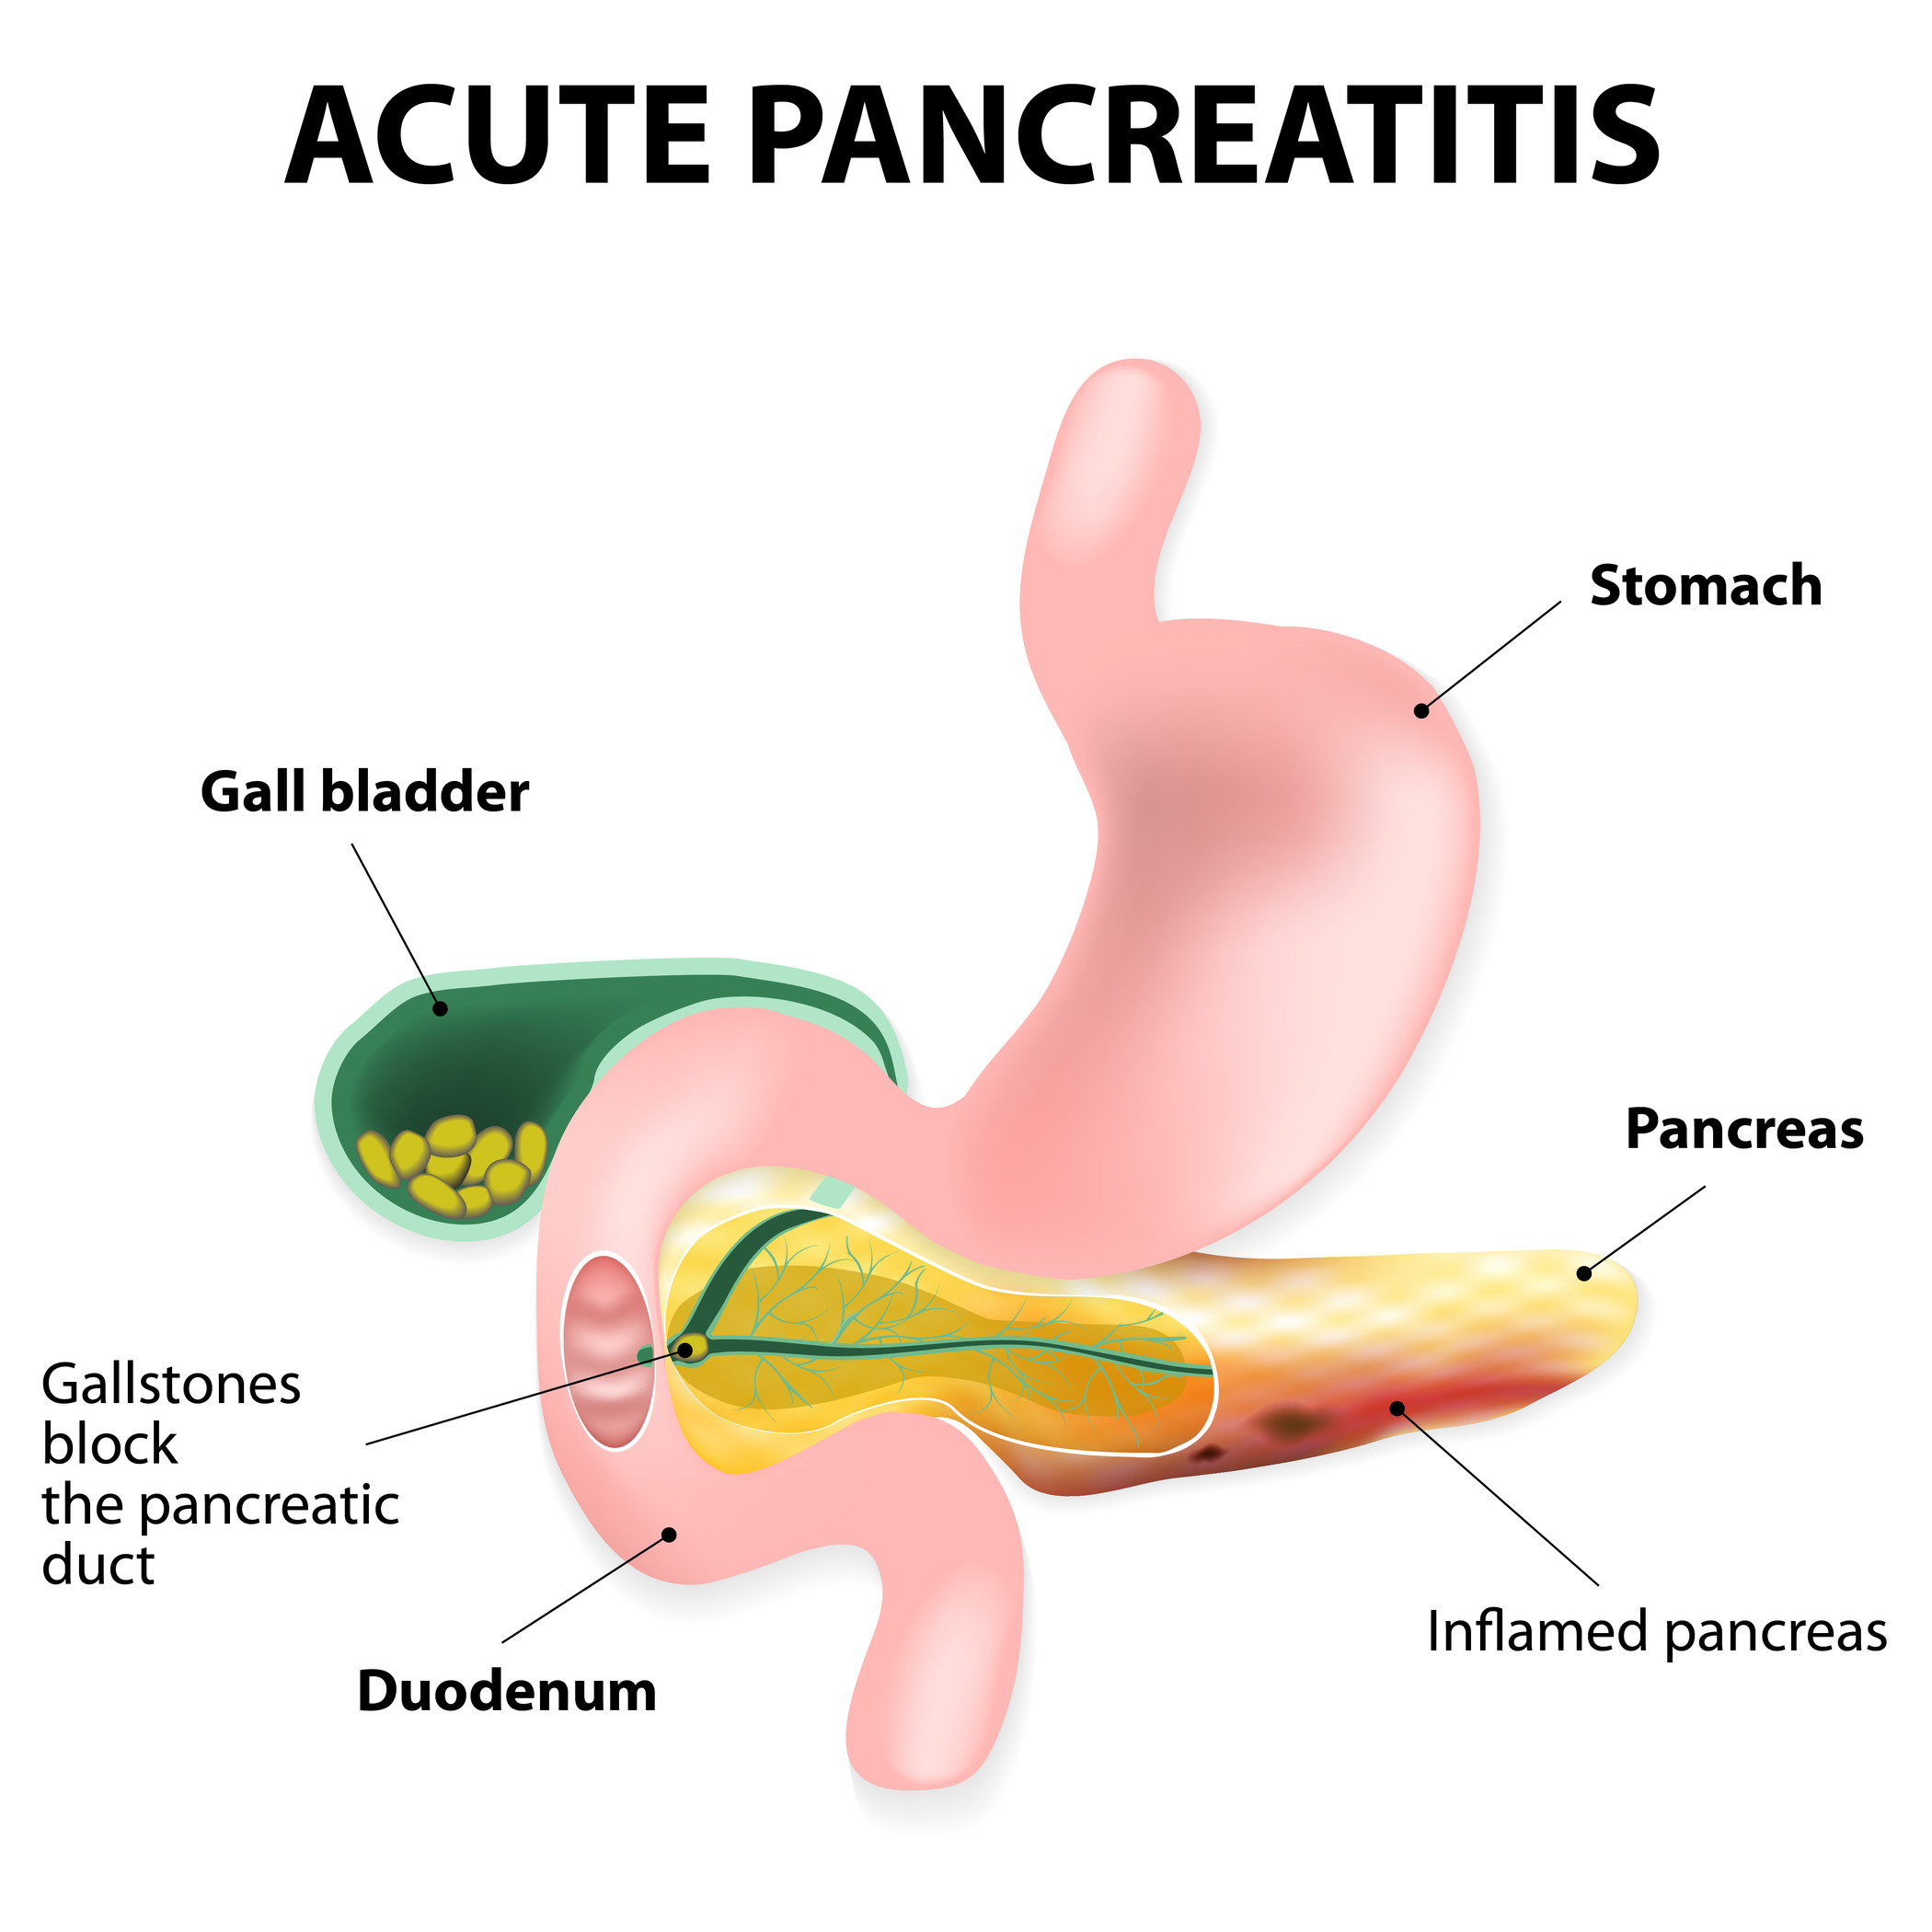
The diagnosis of acute pancreatitis is made by a combination of symptoms, physical exam findings, and laboratory tests including amylase and lipase. If the diagnosis is uncertain, abdominal imaging studies such as a computed tomography (CT) scan may also be necessary.
What are the Symptoms of Acute Pancreatitis?
- Gradual or sudden onset of severe pain in the upper abdomen that may radiate to the back and usually persists for several days.
- Nausea and vomiting
- Fever
What Should I Do If I Think I Have Pancreatitis?
If you are experiencing severe abdominal pain, call your doctor or go to the nearest emergency room. The doctor will take a medical history, perform a physical examination, and draw blood to tests for pancreatic enzymes (amylase and lipase). An ultrasound of the abdomen may be performed to exclude the presence of gallstones. Other abdominal imaging tests such as a CT scan or MRI may also be performed. Endoscopic procedures such as ERCP or EUS may also be warranted in some patients.
Treatment
What is the Treatment for Pancreatitis?
The principles for the treatment of acute pancreatitis are:
- Rest the pancreas by restricting oral intake of food
- Administer intravenous fluids to maintain an adequate blood volume
- Pain Medication
If alcohol is the cause of pancreatitis, strict abstinence from alcohol is recommended. Surgical removal of the gallbladder is indicated when the pancreatitis results from gallstones or gallbladder sludge. If the bile duct is blocked by a gallstone, an ERCP may be required to remove the gallstone.The most important goal in the treatment of chronic pancreatitis is to provide pain relief and prevent progression of disease. If pain is difficult to control, you may be referred to a chronic pain specialist. At times, relief of pain may require endoscopic, radiologic, or surgical treatment.
If your pancreas is found to be unable to provide sufficient enzymes for adequate digestion, you may benefit from enzyme supplements. Also, if your blood sugar level is very high and not controlled by diet or oral medications, insulin may be required. It is important to avoid alcohol. Complete cessation of smoking is recommended as it is a risk factor for progression of chronic pancreatitis and pancreatic cancer. In a few select patients, there is also the option of surgically removing the pancreas to reduce pain and transplanting the islets from the pancreas into the liver to potentially prevent diabetes. Since chronic pancreatitis is also a risk factor for pancreatic cancer, you should speak to your provider about ways to help reduce your risk of developing pancreatic cancer.
Prevention of Pancreatitis
- Gallstone Pancreatitis – surgical removal of the gall bladder
- Alcohol/tobacco induced Pancreatitis – strict abstinence from alcohol and/or tobacco
- Drug Induced Pancreatitis – avoid offending medication
- Hypertriglyceridemia – aggressive lipid-lowering agents
- Avoidance of high fat foods, consuming diets rich in vegetables, and maintaining adequate fluid intake
Author(s) and Publication Date(s)
Vikesh K. Singh, MD, MSc, Pancreatitis Center, Division of Gastroenterology, Johns Hopkins Hospital and Bechien U. Wu, MD, MPH, Division of Gastroenterology, Kaiser Permanente Southern California – Updated December 2012.
Peter A. Banks, MD, MACG, Brigham & Women’s Hospital, Boston, MA – Updated April 2007.
Peter A. Banks, MD, FACG and Saleem A. Desai, MD, Brigham & Women’s Hospital, Boston, MA – Published October 2002.
Source:https://gi.org/topics/pancreatitis-acute-and-chronic/